A wet bed at 2 am can make progress feel far away, particularly when a child has been dry for several nights and then has an accident. But bedwetting treatment outcomes are rarely a straight line. The most useful measure is not one difficult night. It is the gradual pattern: fewer wet nights, smaller wet patches, waking more readily, and growing confidence around sleepovers, school trips and holidays.
Bedwetting, also called nocturnal enuresis, is common in children and is not caused by laziness, poor parenting or a child choosing not to try. Treatment works best when the goal is clear: protect dignity and sleep tonight while building skills that can support dry nights over time.
What bedwetting treatment outcomes look like
A positive outcome can mean different things for different families. For some, it is a child becoming consistently dry without relying on protection. For others, it is fewer accidents, less disrupted sleep and a reliable plan that makes nights away from home feel possible. Both are meaningful progress.
With alarm therapy, early changes may be subtle. A child may start to wake to the alarm, pass less urine before waking, or need less help from a parent. These signs suggest that the brain and bladder are beginning to respond together. Dry nights may follow, but they do not always arrive immediately.
A treatment response is usually assessed over weeks rather than days. A four-week review can help a family see whether the pattern is improving and whether the routine needs adjusting. Recording wet and dry nights, alarm responses and relevant factors such as constipation or illness turns a frustrating memory-based judgement into useful information.
Lasting dryness is often the preferred goal, but it should not be treated as a pass-or-fail test. Some children need more time, another course of treatment or clinical support for an underlying bladder or bowel issue. A return of bedwetting after a dry period can also happen during illness, stress or changes to routine. It is a signal to review the plan, not a reason for blame.
Why alarm therapy can lead to lasting change
Bedwetting alarms are designed to respond at the first sign of moisture. The alarm prompts the child to wake, finish using the toilet and gradually recognise the body signals that occur before a full bladder empties during sleep. This is different from simply managing the wet bed after it happens.
For many families, alarm therapy offers the best chance of sustained improvement because it supports learning rather than only temporary dryness. However, it requires consistency. The first few weeks can be tiring, especially when a child sleeps deeply and a parent needs to help them wake fully.
The details matter. An alarm should be loud or noticeable enough for the child, but the response should remain calm and predictable. Encourage the child to get up, use the toilet if they can, change into dry clothing and reset the sensor. Over time, they should take on as much of this routine as their age and ability allow. This builds independence without placing responsibility or shame on them.
Predictive systems may alert before substantial wetting has occurred, rather than after a sensor is fully wet. For some families, this can reduce the practical impact of an accident and make it easier to act on the alarm quickly. The right system depends on the child’s sleep patterns, the household’s routine and whether the family can commit to using it consistently.
The factors that shape results
No treatment can promise the same result for every child. Age, depth of sleep, bladder capacity, family routines and the presence of daytime symptoms can all affect the pace of progress. A child who is motivated to use an alarm may still need close parental support at first, particularly if they do not wake independently.
Constipation deserves particular attention. A full bowel can press on the bladder and contribute to both daytime urgency and night-time wetting. Regular bowel habits, adequate daytime fluids and appropriate clinical advice can make a real difference to treatment success.
Fluid routines also need balance. Children should drink regularly during the day rather than becoming dehydrated in an attempt to avoid wetting. Reducing drinks immediately before bed may help some families, but strict restriction is not a treatment on its own and can create unnecessary anxiety. Caffeinated drinks should be avoided by children, especially later in the day.
Emotional wellbeing matters too. Bedwetting can make children worry about being found out by siblings or friends. Discreet absorbent sleepwear and waterproof bedding can protect the mattress while reducing laundry and late-night disruption. This protection is not a replacement for treatment, but it gives families breathing space to continue a treatment plan without every accident becoming a crisis.
Measuring progress without pressure
A simple record can make outcomes clearer. Note whether the night was wet or dry, when the alarm sounded, whether the child woke, and whether they used the toilet afterwards. It can also help to record bowel movements and daytime symptoms. Keep the tone neutral: this is health information, not a behaviour chart.
Look for trends across several weeks. Examples of useful progress include fewer wet nights, later wetting episodes, smaller amounts of urine, a child waking before the alarm, or a child responding more independently. One wet night after several dry nights does not erase the progress that came before it.
Praise effort rather than outcomes a child cannot fully control. A parent might say, “You got up and reset the alarm – that is exactly what helps your body learn.” Avoid rewards or consequences based solely on dry nights. They can make a child feel responsible for a body process that is still developing.
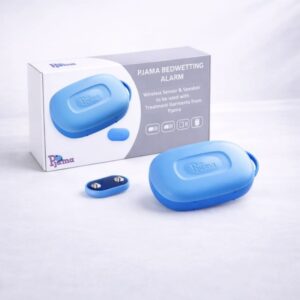
Connected treatment tools can make this tracking easier. Systems such as Pjama DryGuardians combine alarm therapy with progress monitoring, allowing families to see patterns and, where appropriate, share treatment information with clinicians. Clear data can support more personalised care than relying on a recollection of a particularly hard week.
When to seek professional advice
Speak to a GP, school nurse or continence specialist if bedwetting begins suddenly after a child has been dry for at least six months, or if it occurs alongside daytime wetting, urgency, pain when passing urine, recurrent urinary infections, excessive thirst, snoring or constipation. These symptoms may need assessment before or alongside alarm treatment.
Professional advice is also valuable if a child has used an alarm consistently without meaningful improvement, if sleep disruption is becoming unmanageable, or if the emotional impact is growing. A clinician can review bladder and bowel habits, discuss treatment options and help decide whether a different approach is appropriate.
For adults who wet the bed, assessment is particularly important. Adult bedwetting may have a range of causes and should not be managed in silence. Dignified protection can reduce immediate stress, while a healthcare professional can help identify the right next step.
Building a plan your family can keep
The most effective plan is one that fits real family life. Choose a start period when routines are relatively settled, explain the process in simple language, and make sure the child knows they are not in trouble. Keep clean sleepwear and bedding close by so night-time changes are quick and low-key.
If a sleepover or school trip is approaching, protection can preserve confidence while treatment continues at home. There is no need to delay friendships, travel or independence until every night is dry. The aim is to give a child practical security now and a realistic route towards lasting improvement.
Progress often begins quietly: a quicker wake-up, a smaller accident, a child who feels able to pack for an overnight stay without worry. Notice those changes. With consistent support, useful data and the right clinical guidance when needed, each small step can make night-time feel calmer and more manageable.