A wet bed at 2 am can quickly become everyone’s problem: interrupted sleep, extra washing and a child who worries that they have done something wrong. A bedwetting treatment plan for parents should reduce that pressure from the first night, while creating a realistic route towards lasting dry nights. Bedwetting is common, it is not a child’s fault, and it can be treated with the right support.
The most effective plan usually has two jobs. First, protect sleep, bedding and confidence now. Second, use evidence-based treatment to help the child recognise and respond to a full bladder over time. These jobs work better together than either does alone.
Start with a calm, practical baseline
Before changing routines, spend one to two weeks noticing the pattern. Record dry and wet nights, what time wetting happens where possible, bowel habits, daytime drinks and any daytime urgency or leaks. This is not about monitoring a child closely or making them feel watched. It gives you and, if needed, a healthcare professional useful information about what may be contributing.
Keep the language neutral. Say “we are working on this together” rather than asking why they did not wake up. Children do not wet the bed because they are lazy, attention-seeking or drinking too much water. Many sleep deeply, produce more urine overnight, have a bladder that is still developing, or experience a combination of these factors.
If your child is old enough, involve them in the plan. They might help choose protective sleepwear, reset an alarm, or mark effort on a progress chart. Ownership supports independence. The child should never be expected to manage wet sheets alone in the middle of the night.
Build the bedwetting treatment plan around daytime habits
Night-time progress often starts during the day. Encourage regular drinks spread across the day, rather than restricting fluids. A child needs enough to drink for healthy bladder function, concentration and energy. Many families find it helpful to aim for regular toilet visits, including before bed, without forcing repeated ‘just in case’ trips.
Constipation deserves particular attention. A full bowel can put pressure on the bladder and make both daytime and night-time wetting harder to manage. Hard stools, painful bowel movements, infrequent stools or soiling are all reasons to speak with a GP or continence professional.
It can also help to reduce drinks containing caffeine, such as cola, tea, coffee and some energy drinks, especially later in the day. This is a sensible adjustment, not a punishment. Avoid turning the evening into a stressful countdown to bedtime.
Praise actions that your child can control: using the toilet before bed, helping set up their alarm, following their drink routine or putting clean protection ready for the evening. Avoid rewards based solely on dry nights. A dry night is an outcome, not a behaviour a child can simply choose.
Protection for tonight supports treatment tomorrow
Treatment requires consistency, and consistency is difficult when every wet night means stripping a bed and searching for clean bedding. Discreet, absorbent protection gives families breathing room. It can make sleepovers, school trips, holidays and shared bedrooms feel possible again.
Choose washable sleepwear or bedding protection that is comfortable, absorbent and waterproof, with a fit that does not feel bulky or infantilising. Keep a simple night-time set-up: spare pyjamas, a towel or protector, and clean bedding nearby. The goal is a calm change and a return to sleep, not a long disruption.
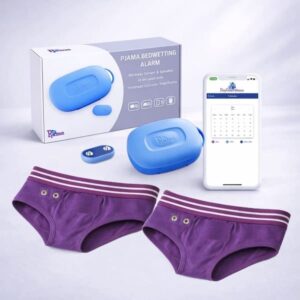
Protection is not giving up on treatment. It prevents bedwetting from taking over family life while treatment is underway. Pjama’s reusable protective sleepwear and bedding are designed for exactly this balance: dignity and comfort now, with less laundry pressure for parents.
Use alarm therapy consistently
For many school-age children who wet the bed regularly, an enuresis alarm is a first-line, evidence-based treatment. The alarm is triggered by the first drops of urine. Over repeated nights, it helps the child learn to wake to bladder signals, hold on, or get to the toilet before wetting.
Alarm therapy takes commitment. It is not usually a quick fix, and the first few weeks can be tiring. A parent or caregiver may need to wake with the alarm, make sure the child is fully awake, and guide them to the toilet. Simply switching the alarm off and putting the child straight back to bed does not build the same learning response.
A reliable routine matters. Fit the sensor correctly each night, test the alarm before bed and respond promptly when it sounds. Change wet clothing or protection, use the toilet, reset the system and return to bed calmly. There is no need for lectures, disappointment or extensive discussion at 3 am.
Many families begin to see a change within several weeks, but progress is individual. Look for smaller signs too: later wetting, smaller wet patches, waking more readily, or dry nights appearing more often. A four-week review is useful for checking whether the system is being used consistently and whether the approach needs adjustment.
Alarm treatment is generally continued until the child has achieved a sustained run of dry nights, often around 14 consecutive dry nights. If there is no meaningful progress after a consistent trial, speak to a continence clinician or GP rather than assuming your child has failed. The fit of the sensor, the timing of the alarm, constipation, sleep patterns and daytime bladder symptoms can all affect results.
When an alarm may not be the right first step
An alarm works best when the child and caregiver are ready to commit to it. It may be less suitable during a period of major family disruption, when sleep deprivation would be unsafe, or if there is no adult available to help the child wake initially. Short-term solutions may be more appropriate for a camp, school trip or special occasion.
A GP may discuss medicine such as desmopressin for selected children, particularly where rapid short-term dryness is needed. It can be helpful, but it does not teach the waking response in the same way as an alarm. It must be used under clinical guidance, including clear advice about fluid intake and safety.
Know when to ask for clinical support
Most children who wet the bed are otherwise well. Still, some patterns need assessment. Contact a GP or continence service if bedwetting starts again after your child has been dry for at least six months, or if there are daytime accidents, urgent or frequent urination, pain when passing urine, recurrent urinary infections, constipation, excessive thirst, weight loss, snoring or major sleep disruption.
Seek advice sooner if bedwetting is causing significant distress, affecting school attendance or stopping your child from joining normal activities. Support is not only for severe symptoms. It is also for families who are exhausted and need a structured plan.
A clinician can check for underlying causes, help distinguish night-time-only bedwetting from broader bladder and bowel issues, and advise on the most appropriate treatment pathway. Connected treatment systems that track alarm responses and progress can also make follow-up more focused, particularly when families need guidance between appointments.
Make progress visible without making it personal
Use a simple record that the child understands. Mark alarm use, toilet routines and dry nights, but keep it private and matter-of-fact. Do not compare siblings or discuss the chart with relatives without your child’s permission. Bedwetting is a health challenge, not family entertainment.
Expect occasional wet nights even after a period of success. Illness, stress, a late bedtime or a change in routine can all interrupt progress. Treat a setback as information: reset the routine, check practical factors and continue with encouragement.
Your child needs to hear one message more than any other: this is manageable, they are not alone, and they will be supported through every stage. Calm protection tonight and a consistent treatment routine tomorrow can make dry nights feel less like a hope and more like a plan.