A family guide to dry nights should begin with one reassuring fact: bedwetting is common, and it is not your child’s fault. It can still be exhausting. Interrupted sleep, wet bedding, washing, worry about sleepovers and a child’s growing wish for privacy can affect the whole household. The most helpful plan protects everyone’s sleep tonight while building calm, realistic progress towards lasting dry nights.
Start with comfort, not pressure
No child chooses to wet the bed. Night-time bladder control develops at different rates, and bedwetting can occur when the bladder fills before the brain receives or responds to the signal to wake. A family history is common, too. This is a health and development challenge, not laziness, bad behaviour or a lack of effort.
The language used at home matters. Avoid asking, “Why didn’t you wake up?” Instead, try: “Your body is still learning this skill, and we have a plan.” Keep changes discreet and matter-of-fact. A younger child may need more practical help; an older child may want to manage changing clothes and placing laundry in a basket independently. Both approaches can support dignity when led by the child’s needs.
Praise the parts they can control: using the toilet before sleep, helping to set up their alarm, wearing protective sleepwear or recording a dry night. Do not reward or punish the wet or dry outcome itself. A wet night is information, not failure.
Protection for tonight makes treatment possible
When families are sleep-deprived, it is tempting to postpone treatment until life feels quieter. But practical protection can create the breathing space needed to start. A waterproof mattress protector, spare bedding within reach and absorbent, washable sleepwear can reduce the scale of a night-time change.
Choose protection based on your child’s age, volume of urine, sensory preferences and independence. Some children are comfortable in disposable products, while others strongly prefer underwear-like, washable options that feel less medical and make sleepovers easier. There is no single right choice. The goal is comfort, dryness against the skin and fewer disrupted nights for everyone.
Keep the process simple. Put fresh pyjamas and bedding close to the bed, use a dim light, and avoid lengthy conversations at 2 am. Change what is necessary, help your child return to sleep, and speak about it normally the next morning. Turning every wet night into a major event can make anxiety worse.
Build a dry-night routine that fits real family life
A predictable evening routine supports bladder health without making bedtime feel like a clinic. Encourage regular drinks throughout the day rather than restricting fluids all afternoon. Children need enough fluid to stay well, and concentrated urine can irritate the bladder. At the same time, it can help to avoid large drinks close to bedtime and drinks containing caffeine, such as cola, tea and energy drinks.
Aim for regular toilet visits during the day, usually around every two to three hours, followed by a relaxed toilet visit before bed. “Double voiding” can help some children: they use the toilet, complete the usual bedtime routine, then try again just before lights out. It should never become a pressured test. If nothing happens, that is fine.
Constipation deserves particular attention. A full bowel can press on the bladder and make bedwetting, urgency or daytime leaks harder to manage. Look for infrequent bowel movements, painful stools, soiling, tummy pain or stool withholding. Discuss concerns with a GP, pharmacist or continence professional rather than relying on guesswork.
A simple record for two weeks can reveal useful patterns. Note wet and dry nights, bedtime, drinks, toilet visits, bowel movements and any daytime urgency or leaks. Keep it factual and private. The record is there to guide care, not to monitor a child’s performance.
When an alarm can support lasting dry nights
For many school-age children who want to become dry, an enuresis alarm is an evidence-based first-line treatment. The sensor detects the first moisture and sounds or vibrates, with the purpose of teaching the brain to respond to a full bladder over time. It is not a quick fix, and the early weeks often require active parent support.
An alarm tends to work best when the child is motivated, the family can respond consistently and the routine can continue for several weeks. At first, many children sleep through the sound. A parent may need to wake them, guide them to the toilet, help them change if needed and reset the alarm. This is not proof that the alarm is failing. It is a normal part of learning.
Consistency matters more than perfection. Holidays, illness, shared bedrooms and demanding work schedules can make alarm therapy harder, so it is reasonable to wait for a relatively stable period. If a sleepover or school trip is approaching, discreet protection may be the more practical immediate answer while treatment continues at home.
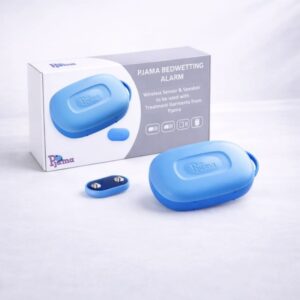
Modern systems can make the process more manageable by combining a treatment garment and sensor with progress tracking and personalised guidance. Pjama’s DryGuardians system is designed to support this structured approach, helping families see patterns rather than relying on memory after a tired morning. A four-week review can be particularly useful: look for earlier waking, smaller wet patches, more dry nights or improved response to the alarm, not only a perfect result.
Give your child a real role in the plan
Children are more likely to engage when they have meaningful choices. Let them choose where spare clothes are kept, whether they prefer a vibration or sound setting where available, and how they want to track progress. Older children may wish to reset their own alarm or manage the laundry. Respect that independence while offering help when needed.
Be careful not to make siblings part of the treatment team unless the child wants that. Privacy is valuable, particularly as children approach secondary school. For sleepovers, pack protection in an ordinary overnight bag, plan a discreet changing option and remind your child that leaving early is always allowed. Confidence often grows when there is a practical backup plan.
Know when to seek clinical advice
Bedwetting is often manageable at home, but some signs need professional assessment. Contact a GP or continence clinician if bedwetting begins suddenly after your child has been dry for at least six months, or if it comes with any of the following:
- pain or burning when passing urine, fever, blood in urine or recurrent urinary infections;
- new daytime wetting, frequent urgency, weak flow or difficulty emptying the bladder;
- marked thirst, unusual tiredness, weight loss or changes in appetite;
- significant constipation, snoring or breathing pauses during sleep;
- distress, bullying, anxiety or a family routine that is no longer coping.
Clinical advice is also worthwhile when an alarm has been used consistently but progress has stalled, or when bedwetting is affecting attendance at trips, relationships or self-esteem. A clinician can assess bladder and bowel habits, discuss alarm therapy or medicine where appropriate, and make sure other causes are not being missed.
Make progress visible, but keep it kind
Dry nights may arrive gradually. One child begins waking before wetting; another has smaller accidents or longer dry stretches. These are meaningful signs of learning. Review the record every few weeks, decide together what is helping, and adjust one thing at a time.
The aim is not a perfectly controlled childhood. It is a child who feels safe, supported and confident that their family has a practical plan. With protection for the difficult nights, a steady routine and the right clinical support when needed, progress has room to happen without shame.